| Severe ("Full Premium Unlock") AR |
- Severe symptoms: Paroxysmal nocturnal dyspnea, orthopnea, pulmonary edema, and chest pain.
- Signs of heart failure: Tachycardia, displaced apical impulse, S3 gallop, and peripheral edema.
- Arrhythmias: Atrial fibrillation (due to atrial enlargement), ventricular arrhythmias.
- Syncope or near-syncope (from severe hypotension during exercise).
|
- Acute aortic regurgitation (e.g., aortic dissection, infective endocarditis with valve perforation).
- Chronic severe AR with progressive LV dilation and dysfunction (EF < 50%).
- Traumatic valve injury (e.g., blunt chest trauma).
- Ruptured aortic sinus of
Clinical Manifestations and Patient Symptoms in Severe Aortic Regurgitation
Severe aortic regurgitation, particularly when described as a "full premium unlock" condition, represents a critical stage where the aortic valve's incompetence leads to irreversible hemodynamic stress. Patients often progress from asymptomatic phases to debilitating symptoms, with manifestations varying based on disease severity, compensatory mechanisms, and individual physiological reserves. Understanding these clinical presentations is essential for early intervention, as delayed diagnosis in severe cases correlates with poorer outcomes, including heart failure, arrhythmias, and sudden cardiac death. This section explores the symptomatic progression, comparative diagnostic challenges with other valvular diseases, and the role of compensatory adaptations in masking symptoms until advanced stages.
Early vs. Late-Stage Symptoms in Aortic Regurgitation
Symptoms in aortic regurgitation (AR) evolve as the left ventricle (LV) dilates and systolic function declines, transitioning from compensated chronic regurgitation to decompensated severe regurgitation. Early-stage symptoms are often subtle and attributed to other conditions, while late-stage symptoms reflect end-organ dysfunction and hemodynamic collapse. The following distinctions highlight key differences, with an emphasis on severe ("full premium unlock") manifestations.
Early-Stage Symptoms (Mild to Moderate AR)
These symptoms typically emerge when compensatory mechanisms (e.g., LV dilation, tachycardia) maintain cardiac output but begin to fail under stress. Patients may report:
- Exercise intolerance – Reduced stamina during physical activity due to increased cardiac workload.
- Palpitations – Sensation of rapid or irregular heartbeat, often triggered by exertion or emotional stress.
- Mild dyspnea on exertion – Shortness of breath during activities, initially dismissed as deconditioning.
- Fatigue – Generalized tiredness, particularly in the afternoon or post-exercise.
- Nocturnal symptoms – Paroxysmal nocturnal dyspnea (PND) or orthopnea (difficulty breathing when lying flat), indicating pulmonary congestion.
Late-Stage Symptoms (Severe AR – "Full Premium Unlock")
When compensatory mechanisms fail, symptoms become severe and life-threatening, often requiring urgent intervention. Key manifestations include:
- Dyspnea at rest – Persistent shortness of breath even during minimal activity, signaling pulmonary edema or heart failure.
- Angina pectoris – Chest pain due to coronary steal phenomenon (reduced diastolic coronary perfusion) or increased myocardial oxygen demand.
- Syncope or presyncope – Sudden loss of consciousness or near-fainting, often triggered by exertion or standing (due to fixed stroke volume and inability to augment cardiac output).
- Pulmonary edema – Acute, life-threatening fluid accumulation in the lungs, presenting with frothy sputum, orthopnea, and tachypnea.
- Fatigue and cachexia – Severe weakness and weight loss due to chronic heart failure and systemic hypoperfusion.
- Systemic emboli – Rare but possible in severe AR with LV thrombus formation, leading to stroke or peripheral embolization.
- Arrhythmias – Ventricular tachycardia or atrial fibrillation due to LV dilation and electrical remodeling.
Critical Insight: Severe AR symptoms often mimic acute coronary syndrome or decompensated heart failure, necessitating echocardiographic confirmation to avoid misdiagnosis.
Comparative Symptomatic Presentation with Other Valvular Diseases
Aortic regurgitation shares symptoms with other valvular diseases, particularly aortic stenosis (AS) and mitral regurgitation (MR), complicating differential diagnosis. Below is a comparative analysis of key clinical features:
| Feature | Severe Aortic Regurgitation | Aortic Stenosis | Mitral Regurgitation |
|---|
| Primary Pathophysiology | Diastolic backflow into LV | Obstruction to LV outflow | Regurgitant flow into LA during systole | | Chest Pain | Angina due to coronary steal or increased O₂ demand | Classic angina (exertional, relieved by rest) | Rare; if present, often due to LV dysfunction | | Syncope | Exertional syncope (fixed stroke volume) | Syncope at rest or exertion (reduced CO) | Less common; may occur with severe LV dysfunction | | Dyspnea | Progressive dyspnea (pulmonary congestion) | Exertional dyspnea (later-stage LVH) | Orthopnea/PND (LA pressure elevation) | | Fatigue | Chronic fatigue (systemic hypoperfusion) | Fatigue (reduced CO, LVH) | Fatigue (if LV dysfunction progresses) | | Heart Sounds | Decrescendo diastolic murmur (Austin Flint murmur) | Crescendo-decrescendo systolic murmur | Holosystolic murmur (radiating to axilla) | | Pulses | Bounding ("water-hammer") pulses | Pulsus parvus et tardus (weak, delayed) | Often normal; may have displaced apex | | Complications | LV dilation, HF, sudden death | HF, angina, sudden death | AFib, HF, pulmonary hypertension |
Key Differentiators for Severe AR:
- Diastolic murmur (high-pitched, blowing) heard best at the right sternal border (unlike AS, which is systolic).
- Wide pulse pressure (≥60 mmHg) due to hyperdynamic circulation (bounding pulses, head bobbing).
- Absence of radiation (AR murmur does not radiate; AS radiates to carotids; MR radiates to axilla).
Diagnostic Pitfall: Patients with hypertension may present with a systolic murmur mimicking AS, but Doppler echocardiography confirms diastolic flow reversal in AR.
Case Study Summaries: Progression of Severe Aortic Regurgitation
Hypothetical case studies illustrate how symptoms escalate with disease progression, emphasizing the silent chronic phase and acute decompensation triggers.
Case 1: Chronic Severe AR with Compensatory Failure
A 55-year-old male with a history of rheumatic fever presents with a 6-month history of exertional dyspnea and fatigue. He was initially diagnosed with "deconditioning" but now reports orthopnea and paroxysmal nocturnal dyspnea. Echocardiography reveals:
- LV end-diastolic diameter (LVEDD) = 7.0 cm (normal <5.7 cm)
- Ejection fraction (EF) = 45% (normal ≥55%)
- Severe AR with holodiastolic flow reversal in the aorta
- Signs of pulmonary hypertension (RVSP = 50 mmHg)
Symptom Progression:
1. Asymptomatic (2018–2020): Mild AR detected incidentally; no limitations.
2. Mild symptoms (2021): Exercise intolerance, dismissed as stress-related.
3. Moderate symptoms (2022): Fatigue, palpitations, nocturnal dyspnea.
4. Severe decompensation (2023): Pulmonary edema after a viral infection, requiring ICU admission.
Trigger: Myocarditis (infection) worsened LV dysfunction, precipitating acute heart failure.
Case 2: Acute Severe AR with Preserved LV Function
A 40-year-old female with bicuspid aortic valve presents to the ER with sudden-onset chest pain, syncope, and hypotension after a marathon. Examination reveals:
- Blood pressure = 80/60 mmHg (pulse pressure = 20 mmHg)
- Hyperdynamic precordium with a diastolic murmur
- No S3 gallop (unlike chronic AR)
Symptom Progression:
1. Asymptomatic (2019–2023): Known bicuspid valve; no prior symptoms.
2. Acute decompensation (2023): Exercise-induced aortic dissection led to acute severe AR, causing cardiac tamponade.
3. Emergency intervention: Aortic valve replacement + repair performed within 6 hours to prevent death.
Key Insight: Acute severe AR presents with hypotension, syncope, and shock, unlike chronic AR where hypertension and bounding pulses dominate.
Case 3: Severe AR in Hypertensive Patient
A 68-year-old male with long-standing hypertension and diabetes reports progressive dyspnea, angina, and lower extremity edema. Echocardiography shows:
- LVEDD = 6.8 cm
- EF = 30%
- Severe AR with LV thrombus (rare but possible in severe dysfunction)
Diagnostic Approaches and Medical Imaging in Severe Aortic Regurgitation
The accurate diagnosis of a leaking aorta heart valve, particularly in severe aortic regurgitation (AR), relies on a systematic integration of clinical assessment and advanced medical imaging. Early detection and precise characterization of regurgitation severity are critical to guide timely intervention, prevent complications such as heart failure, and optimize patient outcomes. Diagnostic strategies range from bedside evaluations to sophisticated imaging modalities, each offering unique insights into the structural and hemodynamic abnormalities associated with AR. This section explores the step-by-step diagnostic workflow, from auscultation findings to advanced imaging techniques, while emphasizing the role of quantitative measurements in treatment decision-making.
Physical Examination and Auscultation Findings in Aortic Regurgitation
The diagnostic process begins with a thorough physical examination, where auscultation plays a pivotal role in identifying characteristic murmurs and other clinical signs of aortic regurgitation. Key findings include:
- Diastolic Decrescendo Murmur: The hallmark of AR, this high-pitched, blowing murmur is best heard along the left sternal border during early diastole, radiating toward the apex. Its decrescendo pattern reflects the pressure gradient between the aorta and left ventricle (LV) collapsing as blood flows back into the ventricle. The loudness and duration of the murmur correlate with regurgitation severity—softer and shorter murmurs suggest mild AR, while loud and prolonged murmurs indicate severe disease.
- Austin Flint Murmur: A mid-to-late diastolic rumble heard at the apex, this murmur results from aortic regurgitant flow striking the anterior mitral valve leaflet, causing mitral valve closure abnormalities and diastolic flutter. It is more common in chronic severe AR and may mimic mitral stenosis. The presence of an Austin Flint murmur often signifies significant regurgitation volume overwhelming the LV.
- Corrigan’s Pulse (Water-Hammer Pulse): A bounding carotid pulse with a rapid upstroke and collapse, reflecting the wide pulse pressure caused by excessive stroke volume during systole followed by rapid runoff into the LV during diastole. This sign is classically associated with acute severe AR.
- De Musset’s Sign: A nodding of the head with each heartbeat, secondary to the transmitted pulsations in the carotid arteries. This finding is rare but highly specific for severe AR.
- Quincke’s Pulse: Capillary pulsations visible in the nail beds or lips, synchronized with the heartbeat, further confirming pulsus alternans or bounding peripheral pulses.
Additional Physical Clues:
- Traube’s sign: A pistol-shot sound over the femoral arteries.
- Duroziez’s sign: A to-and-fro murmur over the femoral arteries when compressed.
- Hill’s sign: A greater systolic BP in the legs than arms (by ≥20 mmHg), indicating peripheral vasodilation due to increased cardiac output.
Role of Echocardiography in Diagnosing Aortic Regurgitation
Transthoracic echocardiography (TTE) and transesophageal echocardiography (TEE) are the gold-standard imaging modalities for diagnosing and quantifying AR. These techniques provide real-time visualization of valve morphology, regurgitant jets, and hemodynamic consequences, enabling precise grading of severity.
Key Echocardiographic Measurements:
- Color Doppler Assessment:
- Regurgitant Jet Area: The width and length of the color flow jet in the LVOT (left ventricular outflow tract) during diastole. A jet width ≥65% of LVOT diameter suggests severe AR.
- Vena Contracta (VC): The narrowest portion of the regurgitant jet at its origin. A VC width ≥0.6 cm is indicative of severe AR.
- Quantitative Doppler Parameters:
- Regurgitant Volume (RVol): The volume of blood leaking back into the LV per beat, measured via proximal isovelocity surface area (PISA) or volume flow integration. Severe AR is defined by RVol ≥60 mL/beat.
- Effective Regurgitant Orifice Area (EROA): The cross-sectional area of the regurgitant jet, calculated using PISA method or continuity equation. An EROA ≥0.30 cm² confirms severe AR.
- Regurgitant Fraction (RF): The percentage of stroke volume regurgitated, with RF ≥50% indicating severe disease.
- Left Ventricular Remodeling:
- LV End-Systolic Dimension (LVESD): Chronic severe AR leads to LV dilation (LVESD ≥55 mm), increasing the risk of systolic dysfunction.
- LV Ejection Fraction (LVEF): Initially preserved in chronic AR, but LVEF <50% signals decompensated heart failure and warrants urgent intervention.
TEE Advantages:
- Superior resolution for valve leaflet abnormalities (e.g., flail leaflets, perforations, vegetations in infective endocarditis).
- Better visualization of aortic root and ascending aorta for assessing dissection or aneurysm in secondary AR.
- Intraoperative use for real-time guidance during valve repair or replacement.
Comparison of Diagnostic Modalities for Aortic Regurgitation
The choice of imaging modality depends on clinical context, suspected etiology, and need for anatomical detail. Below is a structured comparison of key diagnostic tools:
| Modality |
Purpose |
Pros |
Cons |
| Transthoracic Echocardiography (TTE) |
First-line imaging for AR assessment; evaluates valve morphology, jet severity, and LV function. |
- Non-invasive, widely available, and cost-effective.
- Provides real-time imaging and Doppler assessment.
- Can detect secondary signs (e.g., LV dilation, pulmonary hypertension).
|
- Limited by patient habitus (obesity, lung disease) or poor acoustic windows.
- Less detailed for aortic root or ascending aorta visualization.
|
| Transesophageal Echocardiography (TEE) |
Advanced evaluation of valve anatomy, regurgitant mechanisms, and aortic pathology. |
- Superior image resolution for leaflet abnormalities and aortic root.
- Useful in intraoperative or critical care settings.
- Can guide percutaneous interventions (e.g., valve repair).
|
- Invasive (requires sedation), limiting repeated use.
- Not suitable for all patients (esophageal contraindications).
|
| Cardiac Magnetic Resonance (CMR) |
Quantitative assessment of regurgitant volume, LV mass, and tissue characterization. |
- Superior soft-tissue contrast and volumetric accuracy (gold standard for RVol/EROA).
- Detects myocardial fibrosis or ischemia in chronic AR.
- Non-invasive and no radiation exposure.
|
- Expensive, time-consuming, and less accessible.
- Not ideal for acute or unstable patients.
- Limited Doppler capability compared to echocardiography.
|
| Computed Tomography Angiography (CTA) |
Anatomical assessment of aortic root, valve calcification, and secondary causes (e.g., dissection, aneurysm). |
- Excellent for aortic pathology (e.g., aortic root dilation, intramural hematoma).
- Provides 3D reconstruction for surgical planning.
- Useful in acute AR (e.g., traumatic or dissection-related).
|
- Exposes patients to ionizing radiation.
Treatment Options: From Conservative to Surgical Interventions for Severe Aortic Regurgitation
Severe aortic regurgitation (AR), when left untreated, progressively weakens the left ventricle due to chronic volume overload, ultimately leading to heart failure and reduced survival rates. While asymptomatic patients may initially benefit from close monitoring, symptomatic individuals or those with declining ventricular function often require escalated interventions, ranging from conservative management to advanced surgical or transcatheter techniques. The choice of treatment hinges on symptom severity, left ventricular function, patient comorbidities, and anatomical valve characteristics. This section explores conservative strategies, medical therapies, and surgical interventions—including transcatheter and valve-sparing approaches—while addressing procedural nuances, valve selection, and post-operative care to optimize patient outcomes.
Conservative Management Strategies for Asymptomatic Severe Aortic Regurgitation
For patients with asymptomatic severe aortic regurgitation but preserved left ventricular ejection fraction (LVEF ≥50%), conservative management focuses on delaying disease progression and preventing complications such as endocarditis or heart failure. Lifestyle modifications play a critical role in mitigating symptoms and reducing cardiovascular strain. Sodium restriction (≤2 g/day) helps control blood pressure and fluid retention, while fluid management—avoiding excessive hydration—prevents volume overload. Regular moderate-intensity aerobic exercise (e.g., walking, cycling) improves cardiac efficiency, but high-intensity or competitive sports should be avoided due to the risk of sudden exertional dyspnea or syncope. Patients must receive vaccinations (e.g., influenza, pneumococcal) and prophylactic antibiotics before dental or invasive procedures to reduce endocarditis risk. Smoking cessation and alcohol moderation are also emphasized, as both exacerbate hypertension and cardiac stress.
Close cardiovascular monitoring is essential, with echocardiography every 6–12 months to assess LVEF, left ventricular end-systolic dimension (LVESD), and regurgitant volume. Electrocardiogram (ECG) and blood pressure measurements should be performed annually. Patients should be educated on red flag symptoms, including chest pain, exertional dyspnea, or palpitations, which warrant immediate evaluation.
Medical Therapies in Managing Symptoms and Delaying Progression
Medical therapies aim to reduce afterload, improve ventricular performance, and alleviate symptoms in patients with symptomatic severe aortic regurgitation or those awaiting surgery. Vasodilators (e.g., hydralazine, nitrates) and ACE inhibitors/ARBs are commonly prescribed to lower systemic vascular resistance, reducing regurgitant volume and ventricular workload. Beta-blockers may be used cautiously in patients with concomitant hypertension or tachyarrhythmias to control heart rate and improve diastolic filling. However, medical therapy alone is not curative and does not address the underlying valve dysfunction; it serves as a bridge to surgery or a palliative option in high-risk surgical candidates.
Below is a comparative analysis of key medical therapies:
| Drug |
Mechanism |
Evidence |
Limitations |
| ACE Inhibitors (e.g., Lisinopril, Enalapril) |
Reduces afterload by inhibiting angiotensin II, promoting vasodilation and natriuresis. |
Improves symptoms in symptomatic AR (Class IIa recommendation, ACC/AHA). Studies (e.g., VALIANT) show reduced hospitalization in heart failure patients. |
Hyperkalemia risk, cough, contraindicated in bilateral renal artery stenosis. Limited long-term mortality benefit in isolated AR. |
| Vasodilators (e.g., Hydralazine, Isosorbide Dinitrate) |
Direct arterial/venous dilation reduces regurgitant volume and preload, respectively. |
Effective in acute decompensation (e.g., IV nitroprusside in ICU). Oral hydralazine improves NYHA class in AR (limited RCT data). |
Tachyphylaxis, hypotension, headache. Not recommended as monotherapy for chronic AR. |
| Calcium Channel Blockers (e.g., Amlodipine, Verapamil) |
Reduces afterload (dihydropyridines) or slows AV conduction (non-dihydropyridines). |
Useful in AR with hypertension or atrial fibrillation. Verapamil may improve diastolic function in hypertrophic cardiomyopathy with AR. |
Negative inotropy risk (verapamil), peripheral edema (amlodipine). Avoid in severe LV dysfunction. |
| Beta-Blockers (e.g., Metoprolol, Carvedilol) |
Reduces heart rate and myocardial oxygen demand; may improve diastolic filling. |
Beneficial in AR with hypertension or tachycardia. Carvedilol showed mortality reduction in heart failure (COPERNICUS trial). |
Bronchospasm risk, fatigue, contraindicated in decompensated heart failure (initially). |
Diuretics (e.g., furosemide) are used to manage pulmonary congestion but should be titrated carefully to avoid hypotension or prerenal azotemia, which can worsen renal perfusion in AR. Digoxin may be considered for atrial fibrillation or severe systolic dysfunction but has no direct benefit in isolated AR.
Indications for Transcatheter Aortic Valve Replacement (TAVR) vs. Surgical Aortic Valve Replacement (SAVR)
The decision between TAVR and SAVR depends on anatomical suitability, patient risk, and valve morphology. SAVR remains the gold standard for patients with native severe AR and good surgical candidacy (STS score <8%). However, TAVR has emerged as a less invasive alternative for high-risk or inoperable patients, particularly those with bicuspid valves or complex anatomies (e.g., severe aortic root dilation).
Key Indications for TAVR in Severe AR:
- High surgical risk (STS score ≥8% or prohibitive comorbidities).
- Porcelain aorta or severe aortic calcification (increasing SAVR risk).
- Bicuspid aortic valve with favorable annular dimensions (<27 mm).
- Frailty or poor pulmonary reserve (e.g., severe COPD).
- Prior SAVR failure (e.g., bioprosthetic valve endocarditis).
Contraindications for TAVR:
- Severe mitral regurgitation (unless addressed concomitantly).
- Active endocarditis.
- Unfavorable annular geometry (e.g., severe asymmetry, calcium distribution).
- Pregnancy or untreated coagulopathy.
Risk Stratification Tools:
- Society of Thoracic Surgeons (STS) Predicted Risk of Mortality Score: Used to assess operative risk for SAVR. Scores ≥8% favor TAVR.
- European System for Cardiac Operative Risk Evaluation (EuroSCORE II): Alternative for European populations.
- Multidisciplinary Heart Team Evaluation: Mandatory for shared decision-making, considering patient preferences, life expectancy, and functional status.
Step-by-Step Overview of Surgical Aortic Valve Replacement (SAVR) Procedure
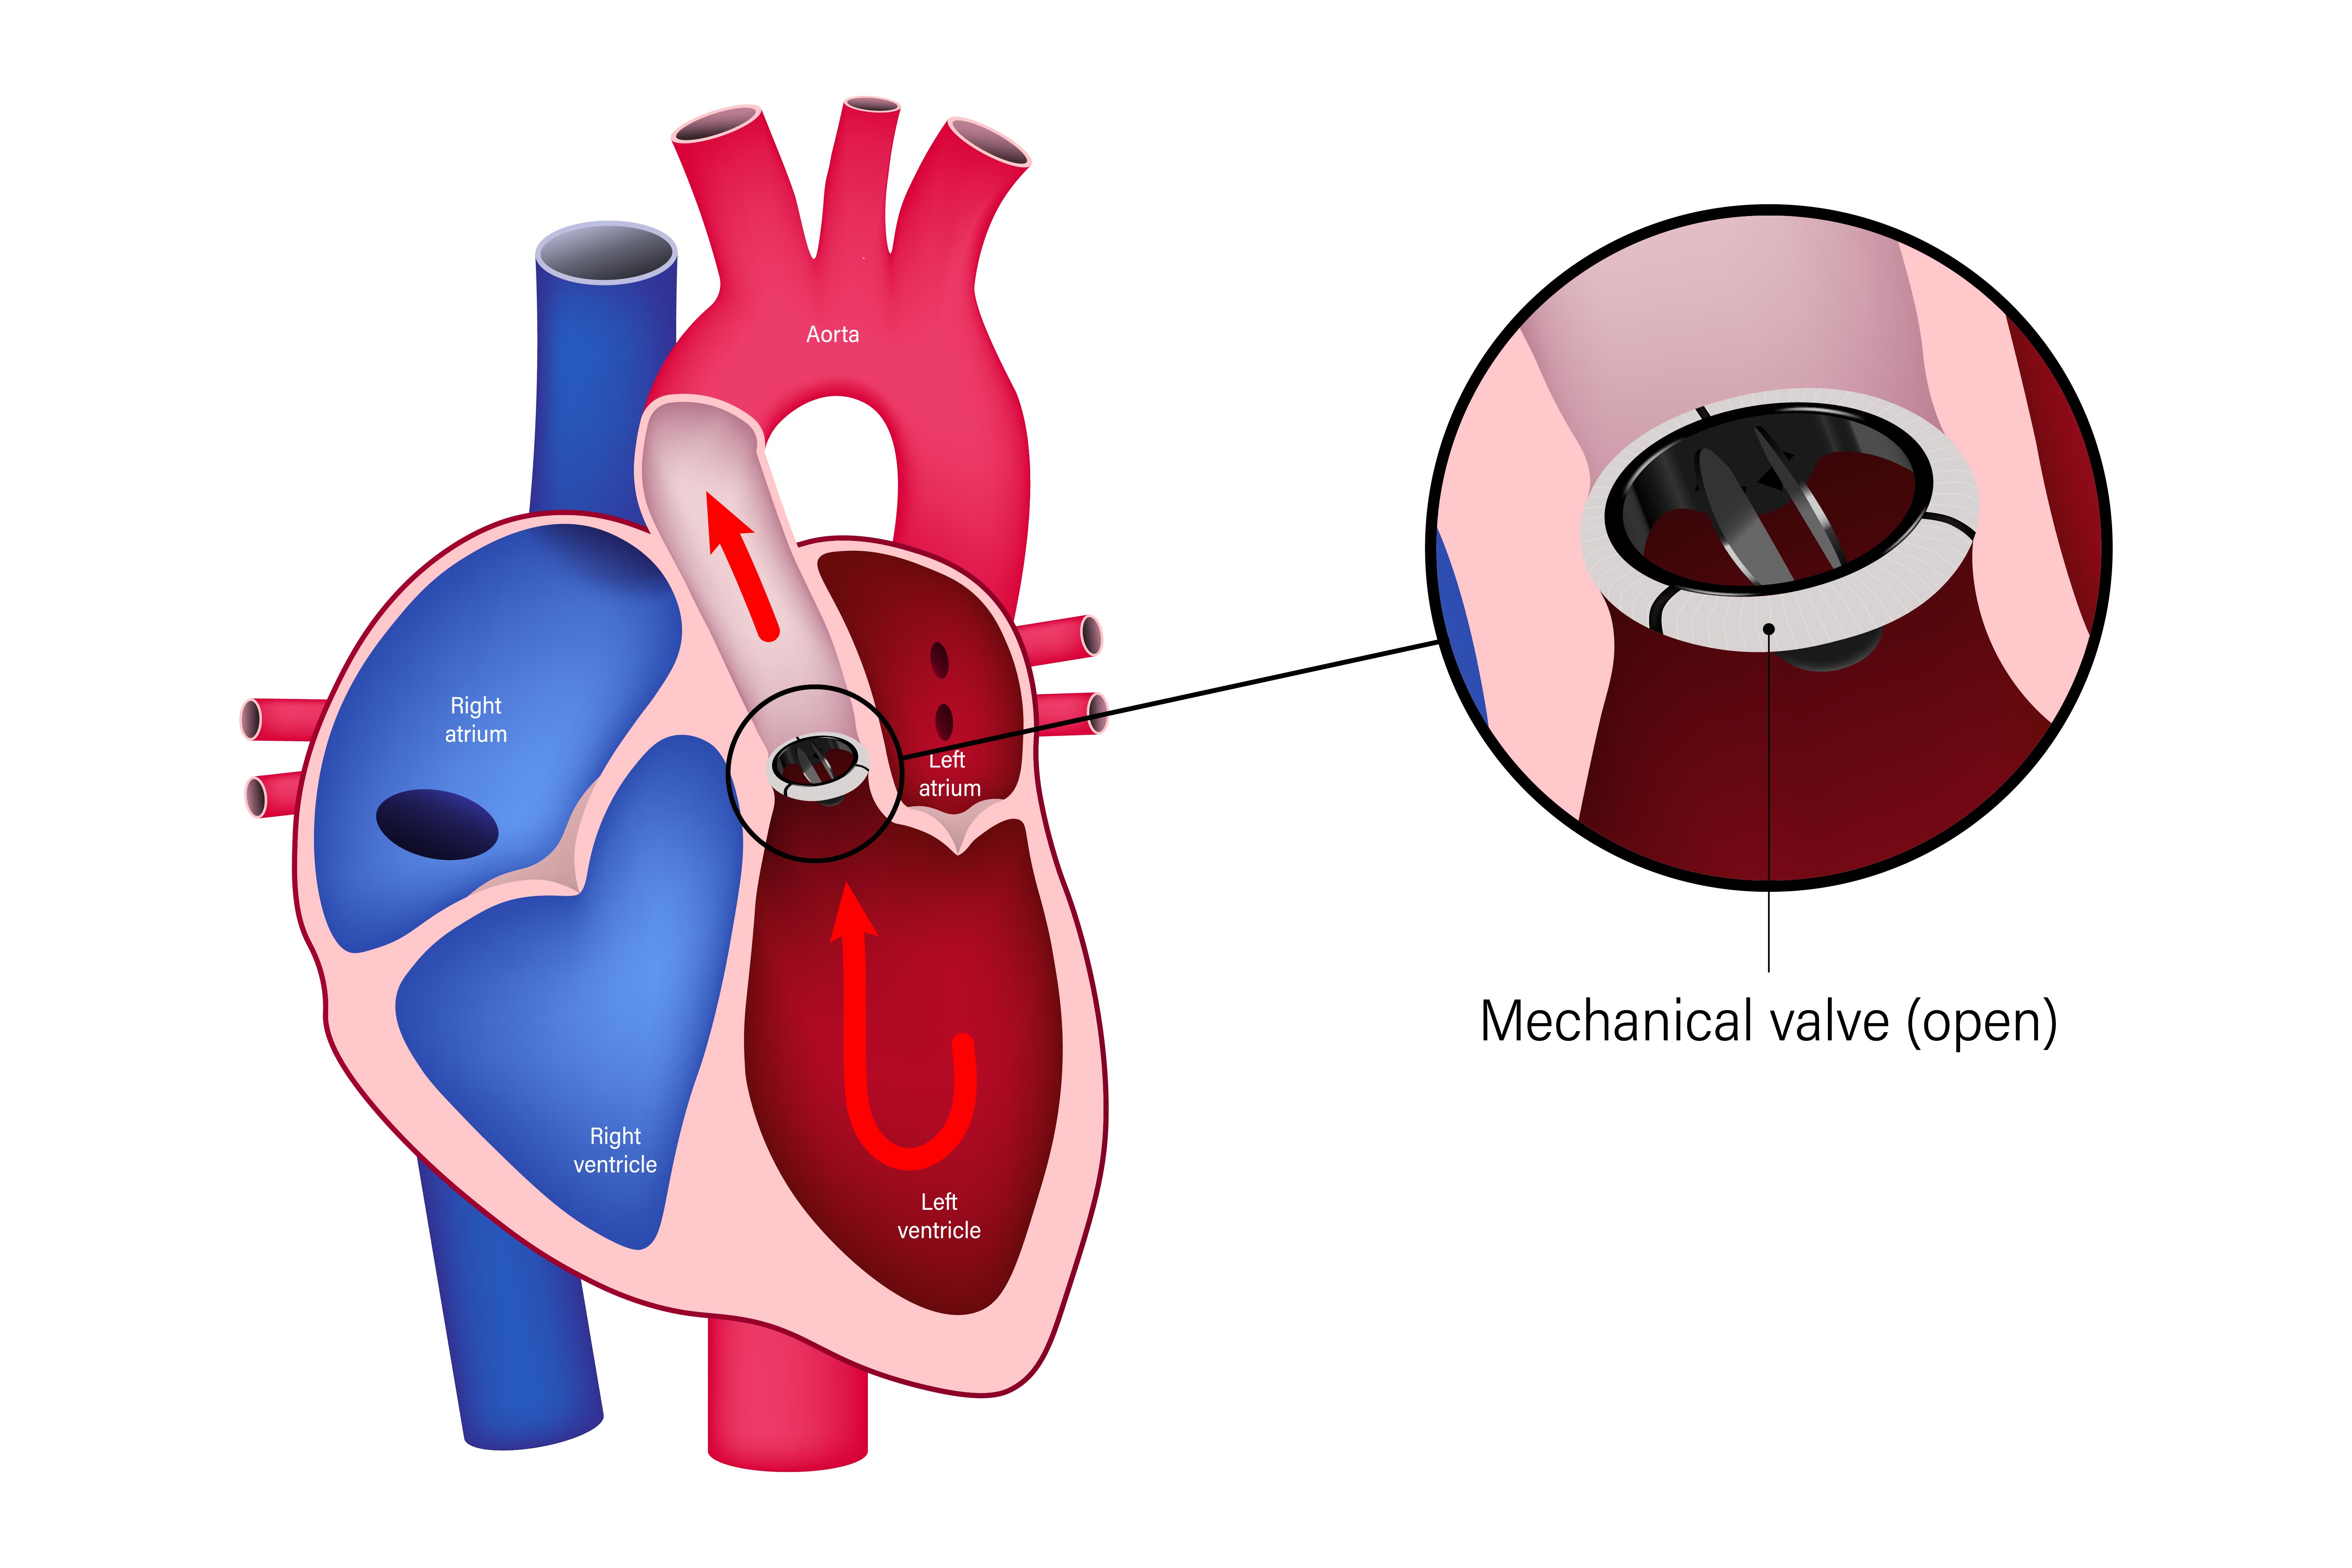
SAVR involves replacing the diseased aortic valve with a mechanical or bioprosthetic valve via sternotomy or minimally invasive approaches. The procedure is divided into preoperative, intraoperative, and postoperative phases, each critical to outcomes.
Preoperative Care:
- Echocardiography: Assesses valve anatomy, LVEF, and regurgitant volume.
- Coronary Angiography: Evaluates concomitant coronary artery disease (CAD).
- Cardiopulmonary Exercise Testing (CPET): Determines functional capacity.
- Blood Work: Includes INR, CBC, renal function, and infectious markers.
- Antibiotic Prophylaxis: Administered 30–60 minutes pre-incision (e.g., cefazolin).
- Anesthesia Assessment: Evaluates for difficult intubation or pulmonary hypertension.
Intraoperative Steps:
1. Sternotomy/Mini-Thoracotomy: Median sternotomy is standard; minimally invasive approaches (e.g., right anterolateral thoracotomy) may be used for select patients.
2. Cardiopulmonary Bypass (CPB) Initiation: Cannulation of aorta and right atrium establishes circulation.
3. Aortic Cross-Clamp: Ischemia time typically <100
A leaking aorta heart valve under full premium unlock conditions is not merely a structural failure—it is a ticking time bomb with symptoms that escalate from barely noticeable to catastrophic within months. From the moment blood begins regurgitating into the left ventricle, the heart’s compensatory mechanisms kick in, masking the severity until irreversible dilation and hypertrophy set in. Diagnostic tools like echocardiography and Doppler ultrasound now provide unprecedented clarity, yet the challenge lies in translating these findings into timely, patient-specific interventions. Whether through medical management, transcatheter repair, or open-heart surgery, the goal remains the same: to restore valve competence before the heart’s compensatory reserve collapses. For patients and clinicians alike, recognizing the warning signs and acting decisively can mean the difference between a full recovery and a life-threatening descent into heart failure. | |
Leave a Comment
Comments are moderated before appearing. The data you submit is processed according to the Privacy Policy of Aamipark.